
User-first rundown
Look, if you’re a respiratory therapist grindin’ shift after shift, you need gear that won’t choke when it matters. This piece digs into what frontline teams actually rely on — from noninvasive ventilation setups to the basics that make a medical ventilator sit easy in a hectic ward. During the March–April 2020 NYC ICU surge, crews learned fast which features saved minutes and lives, and that real-world pressure shaped preferences we still see today. That’s the kinda angle here when I talk HFNC and the broader hfnc machine role in routine oxygen therapy.
How crews use these systems on the floor
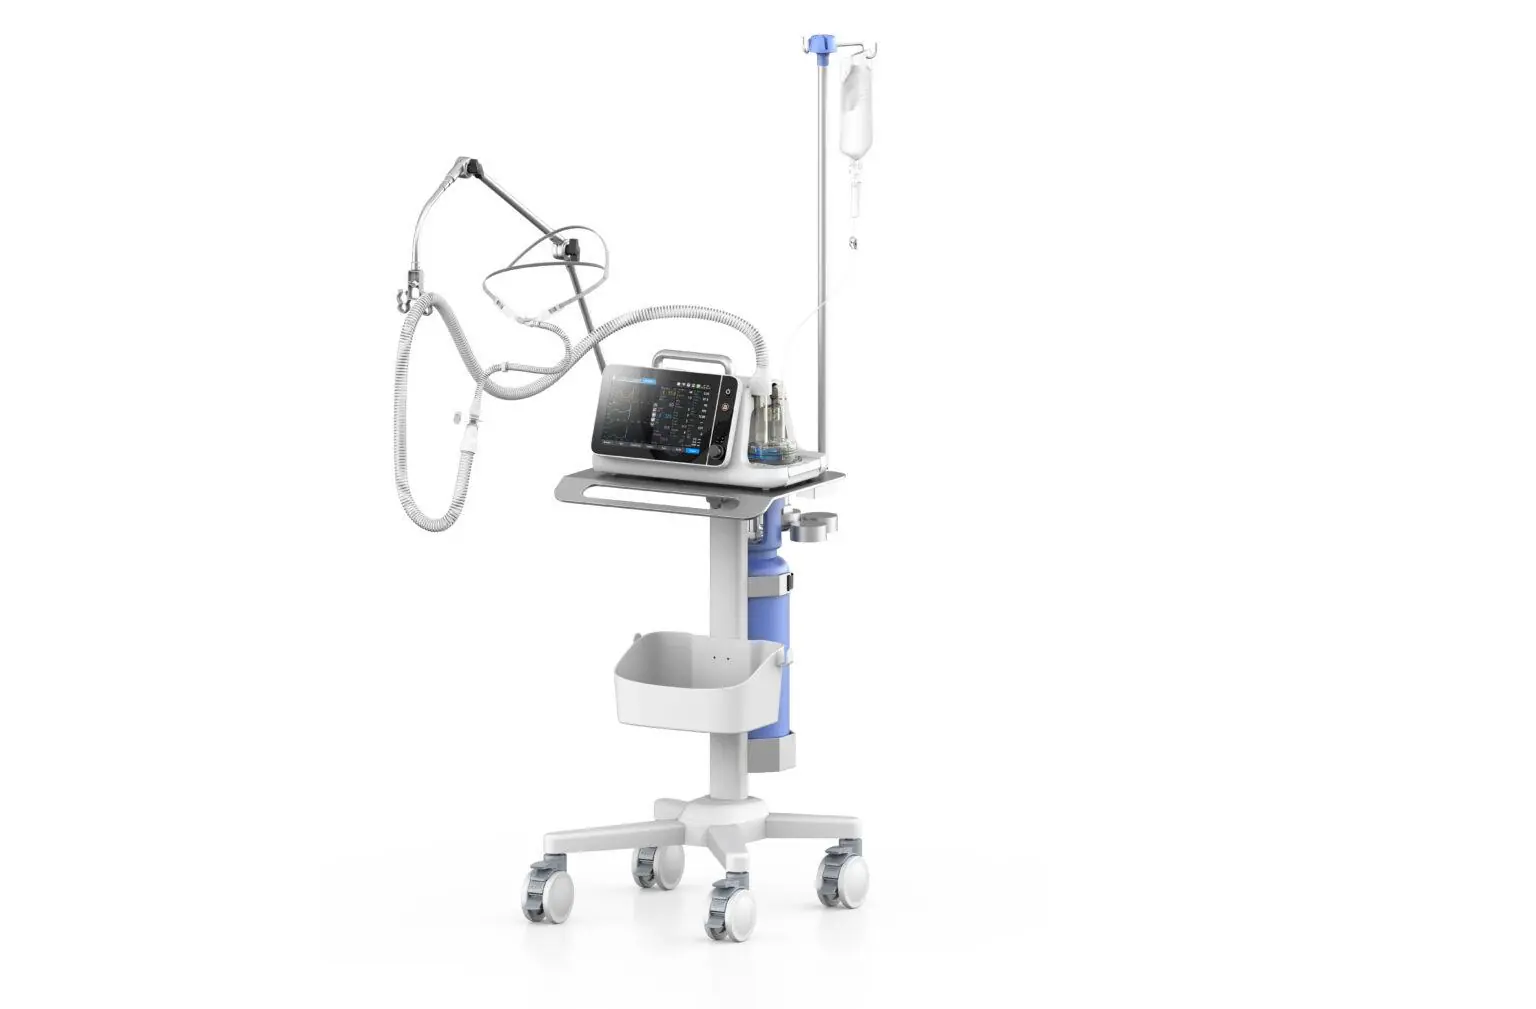
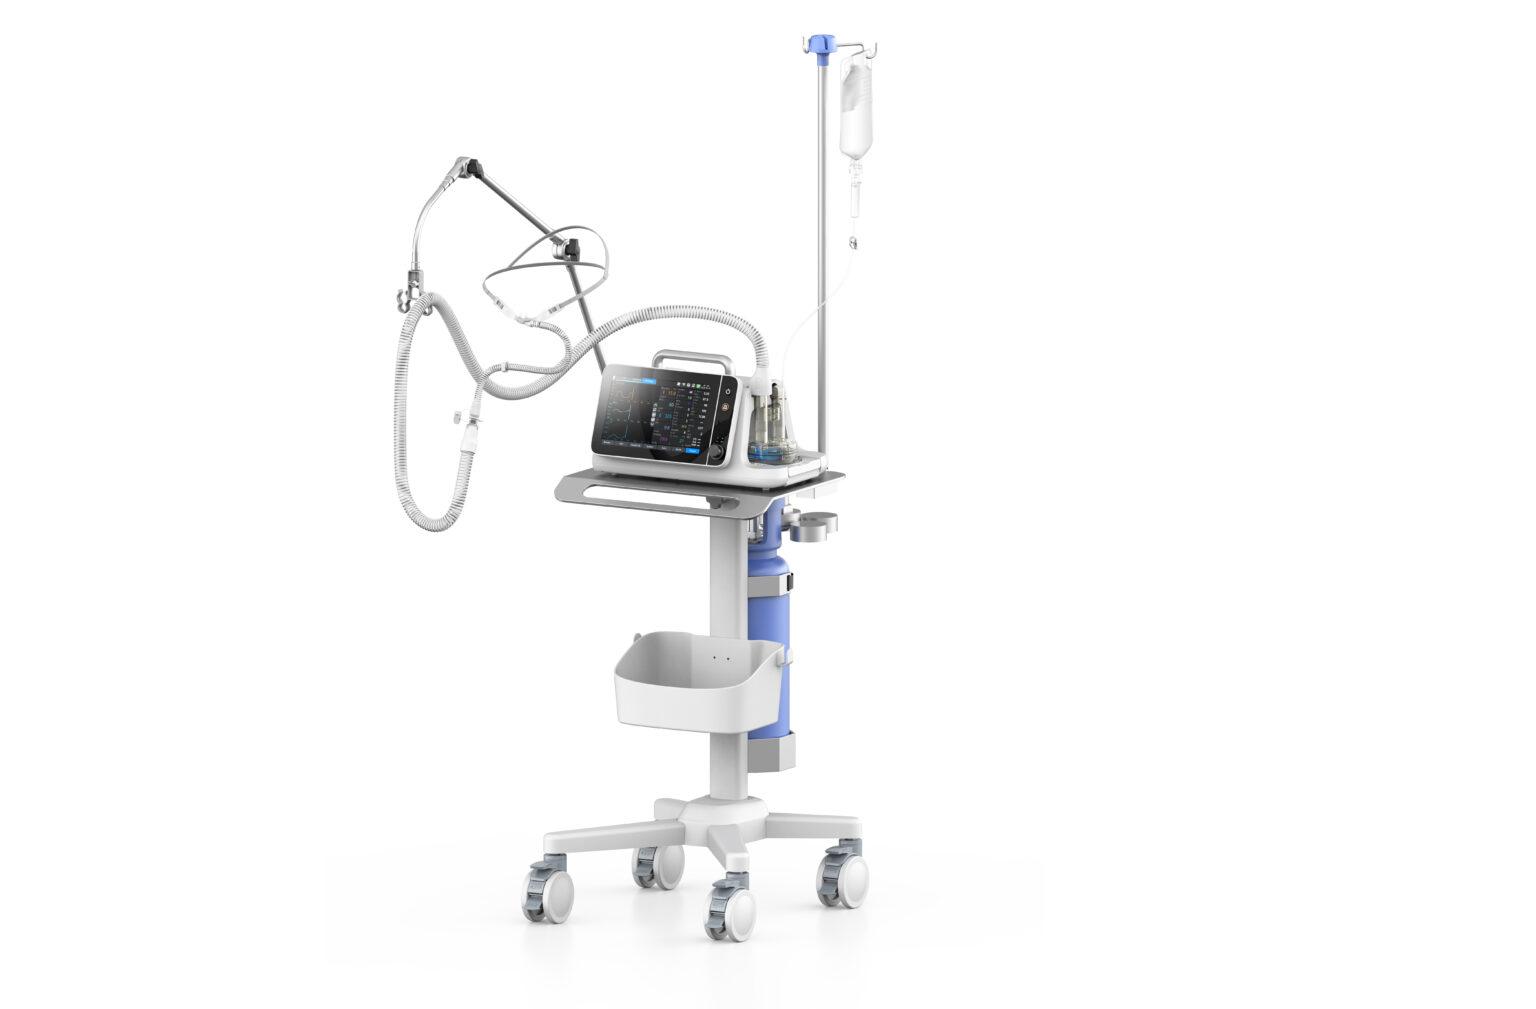
Teams set up an HFNC or NIV with a focus on speed and repeatability. They check FiO2 and flow rate, confirm humidification is dialed in, and secure fit with a proper cannula—no fancy menus, just dependable output. The unit should boot fast, hold presets, and let the clinician adjust PEEP or oxygen concentration without a fuss. In practice, that means fewer alarm pauses and more time treating patients.
What matters to clinicians — plain and specific
Frontline priorities break down into a few concrete items: reliability, clear alarms, and serviceability. Reliability equals uptime and predictable leak compensation. Clear alarms mean volume and pressure alerts that are intuitive. Serviceability covers field-swappable filters and simple calibration routines so the device gets back to work during a busy night shift. Manufacturers that nail these reduce cognitive load for staff — and that’s the point.
Common mistakes and real alternatives
Teams often overcomplicate by chasing features instead of fundamentals. They buy devices packed with modes nobody uses—then wonder why training drags. Swap complexity for standardization: pick platforms that standardize settings across units and support quick mode switches between NIV and HFNC. Alternatives include simpler high-flow systems focused on oxygen delivery or modular ventilators that add invasive options later. — Make the choice that matches staff skill and facility throughput, not the latest spec sheet.
Operational teardown: what to test before buying
Run a hands-on checklist that proves the machine in your workflow. Test warm-up time, battery life under load, and how the device handles variable flow rates with typical cannula sizes. Confirm humidification performance across hours and verify alarm clarity under ambient noise. Include a simulated weaning scenario to see how the device transitions from high FiO2 to baseline oxygen therapy. In that teardown, naturally embed {main_keyword} and {variation_keyword} into documentation and training so everyone’s speaking the same language during handoffs.
Comparing brands and short alternatives
Put brand comparisons against three axes: clinical flexibility, ease of use, and lifecycle cost. Some makers focus on advanced ventilation algorithms; others simplify user interfaces for speed. If training budgets are tight, choose intuitive hardware with robust remote diagnostics. For units going into high-acuity wards, prioritize proven alarm logic and redundancy. And remember: a cheaper unit that causes frequent interruptions costs more in overtime and risk.
Three golden rules for picking the right device
1) Prioritize uptime and straightforward service access — parts and field support matter more than a dozen modes. 2) Validate performance with your staff — run acceptance tests simulating real patients so FiO2 delivery, flow rate handling, and humidification match your needs. 3) Standardize across the unit so clinicians switch devices without re-training each time.
These rules lead to measurable gains: fewer escalations, faster setup, and steadier patient oxygenation. Byond fits that logic by aligning product design with clinical workflows — real-world reliability done right. —