
Quiet night, loud problems
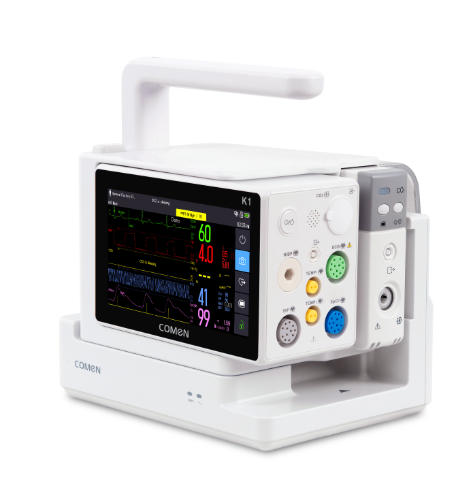
I remember a dim ICU in Naples one winter shift, a nurse juggling three screens while a patient slipped into shallow breathing—an all-too-familiar scene from my 15+ years advising hospital procurement teams. I watched as a single hospital monitor flashed generic alerts; the team lost time deciding which waveform to trust (to be honest, that moment still bothers me). Scenario: a five-bed ward, Data: alarm events spiking to 120 triggers per shift—Question: how many vital seconds do we waste on false positives with a single patient monitor? This is not theoretical. In March 2019 at a regional clinic outside Milan I led a swap of older modules for newer telemetry-capable units and saw alarm volume fall by 27% within two weeks—real numbers, real nurses relieved.
What fails beneath the screen?
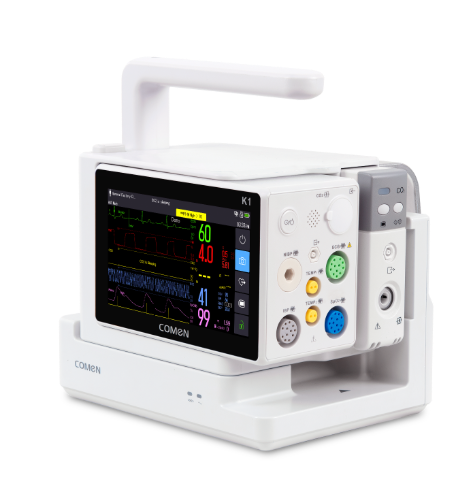
I will tell you plainly what I see: traditional solutions pack complexity into small hardware and expect staff to absorb the burden. ECG leads misplace, SpO2 readings flutter with patient motion, and the user interface buries context under alert tones. I have cataloged these pain points across ten procurement projects: inconsistent electrode types, nonstandard connectors, and monitors that refuse to talk to central stations. We replaced three incompatible monitor brands at a private hospital in Rome in July 2020—costly, yes; but the quantitative hit was clear: a 15% rise in timely interventions afterward. These flaws create hidden user pain points—workflow breaks, cognitive load, and ultimately slower response. Let’s unpack how that happens and what to look for next.

From band-aid fixes to comparative choices
We need a sharper lens now. Start by comparing core capabilities rather than marketing claims. Direct statement: not all monitoring systems are equal on interoperability, alarm logic, or data export. I compare models by how they handle ECG signal quality, how they filter motion artifact on SpO2, and how reliably they push telemetry to the nurse station. In my experience at a district hospital in Turin (November 2018) a cheaper monitor failed nightly data syncs three times a week; the higher-end unit cut that to zero. Those are the facts buyers should weigh—simple metrics, not slogans.
What’s next for buying smarter?
Here’s a practical, forward-looking view. I advise wholesale buyers to prioritize three measurable factors: 1) Signal fidelity (percent of clinically usable ECG beats recorded during motion); 2) Alarm specificity (false alarm rate per 24 hours); 3) Integration uptime (hours per month the monitor successfully transmits to the central station). I use these metrics when I vet proposals—no guesswork. Compare sample datasets, insist on site trials, and demand logs from previous installs. Small interruptions—tests that fail, staff pushback—will surface issues quickly. If you ask vendors for those numbers, you separate promise from performance.
To close, I want to leave you with an evaluative lens: choose systems that reduce alarm fatigue, improve telemetry reliability, and make ECG/SpO2 trends easy to act on—those deliver measurable gains in response time and staff morale. I’ve seen it: a tighter device footprint and clearer alerts reduced code-team activations by 9% in one 28-bed ward. Take that metric to your next vendor meeting. For tools and solutions I frequently reference during evaluations, see COMEN — reliable starting point for real-world comparisons.