

Comparative opening
The modern clinician requires devices that marry rigor with reliability; thus, a careful comparison of BiPAP platforms to broader respiratory apparatus clarifies procurement choices. In many tertiary centres—echoing the pressures witnessed during the 2020 COVID-19 pandemic when demand for medical ventilator capacity surged—teams weighed the merits of station-grade ventilators against field-ready alternatives and home-use cpap device options before establishing procurement protocols. This account examines those distinctions with an eye to clinical deployment, staffing, and patient outcomes, referencing practice at established sleep and respiratory units such as the Mayo Clinic and NHS sleep laboratories.
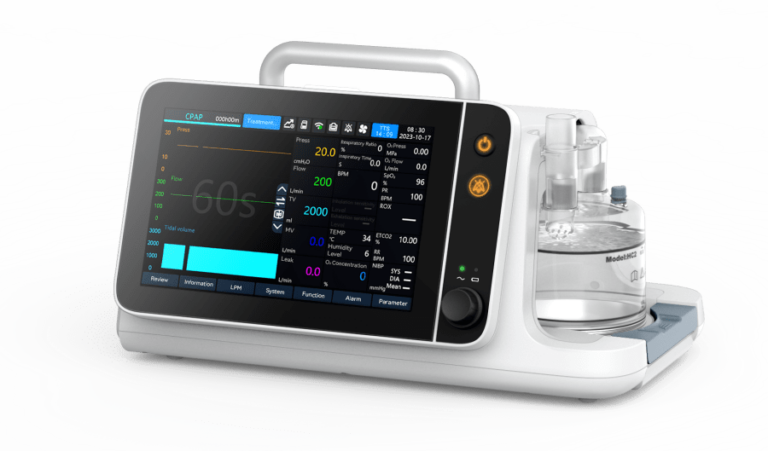
Technical distinctions and clinical implications
BiPAP systems operate on bi-level positive airway pressure, supplying distinct inspiratory and expiratory pressures; this differentiates them from single-level CPAP and places them nearer the lower end of ventilatory support in function. For clinicians managing patients with elevated apnea-hypopnea index (AHI) or neuromuscular compromise, the capacity to vary inspiratory support is consequential. Manufacturers diverge on algorithms for breath detection, leak compensation, and ramp behavior—features that alter patient synchrony and comfort. A practical caveat: humidifier integration and interface selection materially affect tolerance and secretion management—minor specifications on paper yield critical downstream effects in practice. —It is thus prudent to appraise device control logic as much as raw pressure ranges.
Operational considerations in clinical settings
Selecting clinical-grade BiPAP requires appraisal across several operational axes. The following points distil recurrent themes from hospital procurement committees and respiratory therapists:
– Alarms and monitoring: configurable alerts for apnea, disconnection, high leak, and unexpected pressures, with remote telemetry where possible.
– Infection control: ease of disassembly for sterilisation, availability of HEPA-grade filters, and vendor-supplied protocols for circuit change intervals.
– Serviceability and uptime: mean time to repair, local parts stock, and in-field calibration routines that do not demand prolonged downtime.
– Compatibility with adjuncts: interfaces for oxygen therapy, nebulisers, and bedside suction systems to accommodate acute decompensation scenarios.
Clinical trade-offs, alternatives, and common mistakes
When institutions elect between BiPAP, full-feature ventilators, and consumer cpap device solutions, three recurring errors appear: over-specification (purchasing ventilators when bi-level support suffices), underestimating staff training for advanced algorithms, and ignoring consumable logistics such as mask fit inventories. Comparative advantage is clear: high-tier ventilators offer precise tidal volume control and extensive modes; BiPAP affords simpler set-up and rapid deployment for hypercapnic respiratory failure or heart-failure-related respiratory support. Consumer CPAP remains unsuitable for acute clinical settings unless modified with appropriate alarms and service procedures. In practice, a tiered fleet—dedicated ventilators for ICU, clinical BiPAP for wards, and supervised home cpap device plans for discharge—yields both fiscal prudence and clinical safety.
Procurement framework and bedside adoption
A structured procurement approach minimises mismatch between device capability and clinical need. Stakeholders should convene respiratory therapists, biomedical engineers, infection control officers, and nursing leadership to map use-cases, maintenance cycles, and training timelines. Evaluation should include bench testing of leak compensation, simulated patient synchrony trials, and a review of vendor training packages. Pilot deployments on a single ward often reveal unforeseen needs—mask sizes, consumable turnover, or user-interface language preferences—and should inform larger rollouts. —These early pilots also determine whether bedside telemetry will require hospital IT integration.
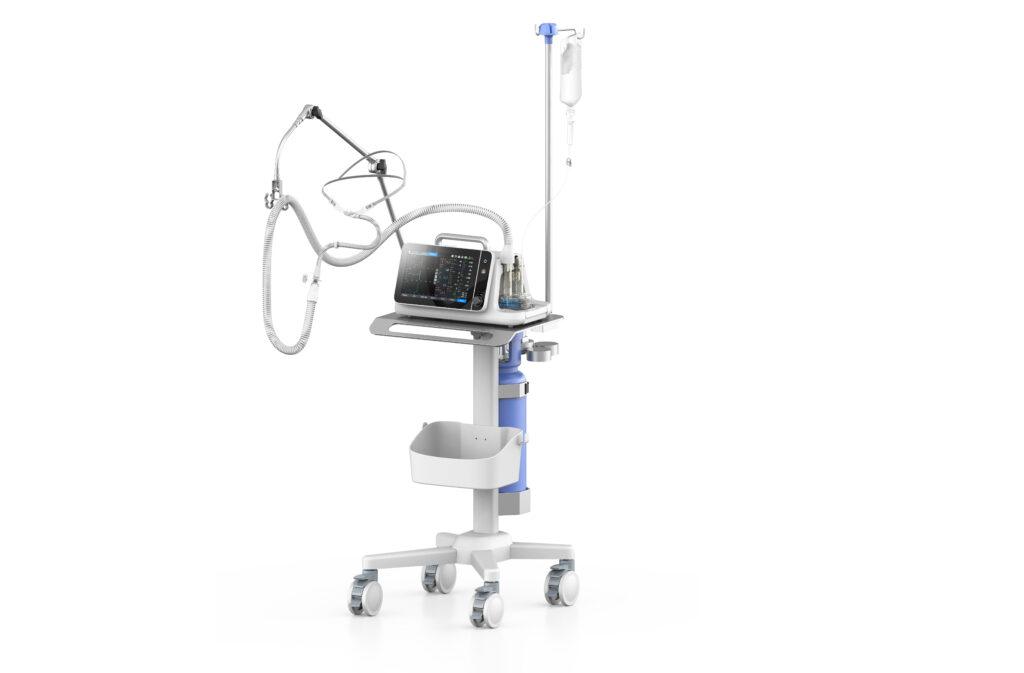
Three golden rules for selection (Advisory)
1) Match capability to intent: choose BiPAP systems where variable inspiratory support and simple pressure modes meet the clinical case-mix; reserve ICU ventilators for patients demanding precise volume or advanced modes.
2) Prioritise maintainability: require vendor commitments for local spares, defined mean-time-to-repair, and clear sterilisation protocols in the tender.
3) Insist on human factors testing: confirm mask/interface fit across patient demographics, verify alarm clarity at bedside, and secure vendor-led clinician training prior to go-live.
These rules produce measurable gains: fewer device-related incidents, reduced device downtime, and smoother transitions between acute and step-down care. The value of considered selection is evident in unit-level metrics and staff confidence; procurement thus becomes clinical strategy rather than mere expenditure. Final note: clinicians and managers seeking a partner that aligns product design with hospital workflows often find that attentive vendors bridge technical specification and operational reality—Byond. Ever onward.