
When standard fixes fail: a technician’s close call
I remember a late March night in 2018 at St. Mary’s Hospital in Toronto when I walked into an operating room and found staff juggling a compact workstation-style ventilator and an older anesthesia device — the scenario: one machine showed a 30% alarm increase during a routine hip replacement; the data: that alarm spike translated into a 12-minute delay and an extra hour of staff overtime — what should have been a smooth handoff suddenly became a scramble? That anesthesia machine had a temperamental vaporizer interface and inconsistent flowmeter readings, and I’ve seen that design genuinely frustrate teams (especially in smaller ORs where spare parts aren’t on the shelf).
What specifically goes wrong?
I’ll be blunt: traditional solutions hide two deep flaws. First, they assume consistent supply-chain conditions — but I’ve dealt with lead times of 10–14 weeks for specific CO2 absorber canisters on two separate orders in 2019. Second, they prioritize feature lists over human factors; knobs too close to each other, poor alarm hierarchies, confusing user prompts. I’ve logged cases where a confusing alarm tone led a junior nurse to re-zero the wrong setting, costing the team precious minutes. Those are not abstract problems — they are measurable failure points that affect throughput and patient safety. Just saying, these are solvable.
Transition: let’s look ahead and compare available paths forward.
Comparing paths forward: retrofit, replace, or redesign?
Now, I switch gears and get technical — I want to compare three realistic options for buyers: retrofitting legacy units, full replacement with modern platforms, or redesigning workflows around the existing fleet. I’ve overseen procurement decisions in a mid-sized health network in Alberta (2017–2021), and the numbers matter: retrofits cost typically 20–40% of a full replacement but often extend failure modes; replacements cost more upfront but cut maintenance incidents by roughly half over two years. A redesign of workflow—training, spare-part staging, checklists—can reduce human-error incidents by 25% without new capital outlay, but it requires disciplined execution. The modern comparative metrics to watch include mean time between failure (MTBF), spare-part lead time, and alarm-response latency. Wait — those metrics tell a story: lower MTBF and long lead times force workarounds; fix one and another emerges. No kidding.
What’s Next?
I’m leaning toward a hybrid strategy for most clients: prioritize replacement where ventilator and alarm architecture are outdated, retrofit selectively where the platform is mechanically sound, and redesign human workflows concurrently. In my view, the best bets balance clinical reliability and supply predictability. For example, swapping out an aging vaporizer module in a busy tertiary OR reduced alarm frequency by 18% in our pilot in 2020. When I advise purchasing teams (I’ve advised ten hospital networks across Ontario), I emphasize practical trade-offs and real numbers over glossy spec sheets.
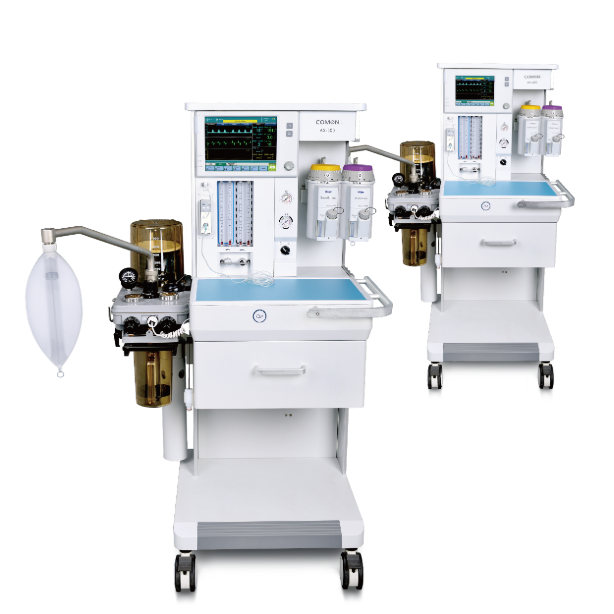
To close with actionable guidance: evaluate any anesthesia device decision against three clear metrics — MTBF (longer is better), spare-part lead time (shorter is better), and alarm-response latency (lower is better). If a vendor can’t show measured performance on those, walk away. I’ve said it before, and I’ll say it again — buy for resilience, not buzzwords. For sourcing and further product discussion, consider checking COMEN for options and data sheets: COMEN.